UK specialists warn Mounjaro could overshadow bariatric surgery
UK obesity specialists have warned that the popularity of Mounjaro and other weight-loss injections risks leaving suitable patients without adequate consideration of bariatric surgery. Their concerns were reported by the Daily Mail on 6 October 2026, alongside figures showing steep falls in private weight-loss operations across the UK.
Gastric sleeve procedures fell by 67 per cent between 2023 and 2025, while gastric bypass operations declined by 79 per cent, according to Private Healthcare Information Network figures cited in the report. Those reductions coincided with growing use of weight-loss medicines, although the figures alone do not establish why patients chose against surgery.
The concern is not that injections have no place in obesity care. It is that their prominence may obscure alternatives for people who experience inadequate weight loss, cannot tolerate adverse effects or cannot sustain private prescription costs.
Professor Ahmed Ahmed, clinical lead for bariatric surgery at Imperial College Healthcare NHS Trust and president of the British Obesity and Metabolic Specialist Society, estimated that NHS activity had also fallen. He put current provision at roughly 5,000 to 6,000 operations a year, compared with 8,000 in 2018/2019.
The debate has particular significance for people with very high starting weights. A substantial percentage reduction can still leave someone living with severe obesity and its associated health risks, specialists told the newspaper.
How Mounjaro and weight-loss surgery differ
Mounjaro contains tirzepatide, which acts on the receptors for two gut hormones, GIP and GLP-1. It helps regulate appetite and blood glucose. Unlike an operation, treatment does not require surgical recovery, but maintaining its benefits may mean continuing medication over the long term.
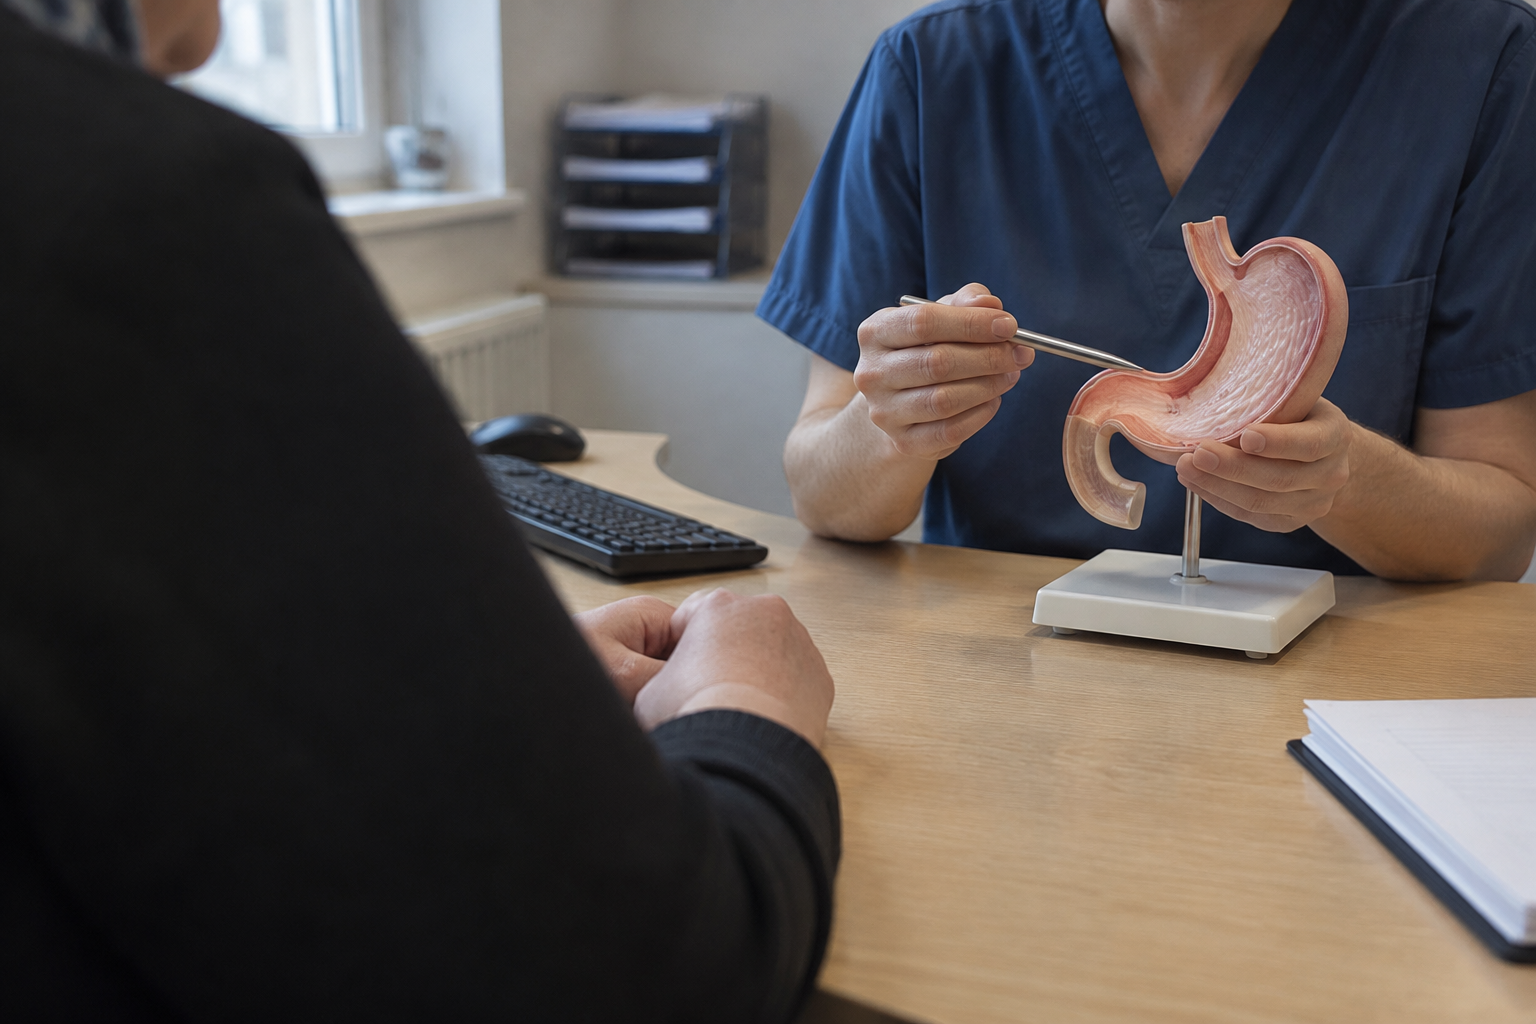
Bariatric procedures change the digestive system. A gastric sleeve removes about 80 per cent of the stomach; a gastric bypass creates a smaller stomach pouch and redirects part of the small intestine. Their effects involve changes in appetite and gut hormones as well as the amount a person can eat.
Professor Omar Khan, a consultant gastrointestinal and bariatric surgeon at St George’s University Hospitals NHS Foundation Trust, told the Daily Mail that surgery produces average weight loss of about 30 per cent over two years, with much of that reduction sustained long term. These are estimates across treatment populations, not a guaranteed result for an individual or a direct comparison with every injection regimen.
Both approaches can offer benefits beyond weight. The report describes improvements in blood glucose and obesity-related conditions with medicines and surgery. Khan said that some patients’ insulin requirements fall rapidly after an operation, and that improvements in blood pressure and obstructive sleep apnoea can follow.
There are important burdens on both sides. Nausea, diarrhoea and constipation can make injections difficult to continue, a practical issue also reflected in patient accounts of Mounjaro side effects. Surgery requires smaller meals, recovery that can take up to six weeks and continuing nutritional care.
Ahmed cited a 2.4 per cent complication rate from the National Bariatric Surgery Registry. Early problems can include infection, wound complications and blood clots; longer-term concerns include hernias, nutritional deficiencies and weight regain. The reported figure should not be treated as a like-for-like safety comparison with medicines, which have different risks and monitoring requirements.
Nor does an operation remove the need for ongoing care. Ahmed described lifelong follow-up as important to maintaining results. Weight regain is also central to decisions about ending drug treatment, and is the subject of research into what happens after GLP-1 treatment stops.
Specialists call for a broader choice of obesity treatments
Alexander Miras, professor of endocrinology at the University of Ulster, told the Daily Mail that a fall in demand for surgery was understandable: many people would prefer medicine to an operation. His concern was whether access to injections, and the ability to keep paying for them, could be sustained.
The report gives differing estimates of how many patients respond poorly to injections, ranging from about 10 per cent to 20 per cent. These should not be read as one settled non-response rate: the article does not provide enough detail about definitions or study populations to reconcile them. Separately, Miras said adverse effects lead some patients to stop treatment.
Dr Rehan Haidry, a consultant gastroenterologist at Cleveland Clinic London, highlighted endoscopic sleeve gastroplasty as another option. This uses instruments passed through the mouth to reduce stomach volume without an abdominal incision; it is distinct from surgically removing part of the stomach.
Haidry said the procedure could produce weight loss of 15 to 20 per cent and was available through the NHS only at selected centres. He put its private cost at about £10,000, comparing that with an illustrative annual injection bill of £3,000. Actual medicine costs vary, and an upfront procedure still entails subsequent care.
For standard bariatric surgery, BOMSS put the NHS operation cost at £5,000 to £5,500. Ahmed estimated that appointments before and after surgery add about £500. These figures help explain the specialists’ interest in long-term value, but are not a complete economic comparison for every patient.
Jack Doughty, speaking for the Obesity Health Alliance, argued that injections should remain part of a wider treatment offering. He also highlighted differences in funding obligations for NICE-approved medicines and other weight-management support, which can shape what services are available.
A proposed trial would compare injections with surgery
Ahmed is seeking funding for a trial comparing injections and surgery on quality of life, weight loss, health benefits and costs. The report gives no confirmed funding award, recruitment date or timetable for results.
Access remains an immediate question. Broad NHS criteria for assessment for bariatric surgery include a BMI of at least 40, or 35 to 39.9 with a significant condition that could improve with weight loss. Meeting a threshold is not an automatic entitlement to an operation: specialist assessment and suitability still matter.
The report also relays anecdotal concerns from BOMSS that uncertainty over eligibility for injections is affecting some local funding decisions. It does not establish how widespread that problem is or announce a change in NHS policy.
For patients, the unresolved issue is therefore more specific than whether injections or surgery are better in general. It is whether services can offer a properly assessed choice, taking account of the weight reduction needed, treatment risks, continuing costs and the care required afterwards.